Questions to Ask a Medical Billing Company Before You Sign (and the Answers That Should Worry You)

A paid claim can still be wrong. CMS's fiscal year 2025 improper-payment fact sheet identifies documentation, eligibility and process problems among the reasons payments may be incorrect. Ask vendors how their workflows prevent these errors and who owns the follow-up. Vague answers can mean avoidable denials, longer A/R and lost revenue.
Headquartered in Texas, Happy Billing provides full-cycle revenue cycle management using agentic AI and expert human auditors. Its services include denial management and A/R recovery, with days in A/R under 35.
The Pre-Signing Question List
Print this list and use it as your vendor scorecard. Ask every question, request supporting documents and carry unresolved items into the contract review. A reassuring conversation isn't a substitute for an obligation you can enforce.
| Topic | Question to ask | Answer to accept | Answer that should worry you |
|---|---|---|---|
| Staffing | Who works our claims, in which roles, and in which country and state? | Named roles, team locations and written disclosure of offshore PHI access | Offshore staff are used, but their countries, roles or access can't be identified |
| Specialty | Which billing rules do you already run for practices like ours? | Specialty-specific workflows, such as anesthesia time units or behavioral health authorization limits | Every specialty is billed the same way |
| Reporting | Which reports do we receive, how often and at what detail? | Monthly payer- and specialty-level reports, written KPI definitions and a live dashboard | Only an aggregate clean-claim rate |
| Denials and appeals | Who owns each denial and appeal, and by what deadline? | Named owners, written deadlines and high-dollar escalation | The clearinghouse handles denials |
| Prior authorization | What are results by payer, specialty, service type and appeal outcome? | Counts requested, denied, appealed and overturned, with an accountable owner | Requests are submitted, but outcomes aren't tracked |
| Underpayments | How do you find and dispute underpaid claims? | Claim-level comparison with contracted or applicable allowed amounts and documented disputes | Only full denials are reviewed |
| Security | Will you sign a BAA and identify every subcontractor with PHI access? | A signed BAA, subcontractor list and prompt contractual incident-notification requirement | An NDA supposedly covers PHI, or compliance is asserted without evidence |
| Exit | How do we leave, and what happens to our data and open claims? | Defined notice, usable claim-level exports and written handling of open A/R | The practice supposedly doesn't need its own data |
| Pay model | How are you paid, and what falls outside the agreed scope? | A written model, exclusions and a clear proposal before signing | Guaranteed total collections or pressure to sign immediately |
Outsourcing shouldn't mean surrendering financial oversight. The Blue Sage Tax outsourcing guide from Blue Sage Tax & Accounting Inc. offers useful context for evaluating outsourced accounting alongside billing. Keep the responsibilities distinct: your accountant reconciles the business's finances; your billing partner must explain each claim's path to payment.
Signing rule: Accept evidence, not adjectives. Mark unsupported answers as unresolved, even when the sales presentation sounds convincing.
Who Works Your Claims, Where, and With What Training
Book a free 30-minute call with a billing specialist to discuss which responsibilities your practice should retain or outsource.
US practices only.
Ask who handles your claims. Request the roles responsible for eligibility, charge capture, coding, submission, payment posting and appeals, together with each team's country and state. Offshore access isn't automatically a reason to reject a company. Undisclosed access is.
Ask whether coding staff hold current AAPC credentials, such as the CPC, and how supervisors audit coding accuracy against applicable coding standards and payer requirements. MedicalVirtual's hire medical coder page is useful when comparing a dedicated coding role with a broader billing engagement. Hiring a coder alone doesn't assign responsibility for unpaid claims.
Test specialty fit through financial consequences
An anesthesia vendor should explain time-unit validation and concurrency documentation. A behavioral health partner should demonstrate authorization-expiration and approved-visit controls. An orthopedic partner should show how global-period reviews prevent unsupported billing and avoidable payment disputes.
Use our specialty billing workflows to frame questions around your practice rather than accepting a generic specialty list.
We integrate with eClinicalWorks, Athena Health, EPIC, NextGen, ModMed and other EHR systems. Our coders and compliance team are trained on both SB 1264 and the federal No Surprises Act.
The acceptable answer names roles, an account lead and an escalation route. It also explains who covers absences and who can resolve a stalled claim without sending your administrator through multiple departments.
Monthly Reports to Demand and the Numbers They Show
| Metric | What it reveals | How often |
|---|---|---|
| First-pass acceptance rate | Claims accepted without rejection, not necessarily paid | Monthly, by payer |
| Denial rate by reason and payer | Where payment fails and which denials were preventable | Monthly, with a written denial definition |
| Appeal overturn rate | Appeal results, alongside submission and resolution times | Monthly, by payer and denial reason |
| A/R aging buckets | Outstanding balances grouped by time unpaid | Weekly or monthly |
| Timely-filing losses | Revenue written off because submission deadlines expired | Monthly, claim by claim |
| Net collection rate | Collections relative to the applicable allowed amount | Monthly, by payer and specialty |
| Unapplied cash | Received payments not yet assigned to accounts | Weekly |
Every rate needs a numerator, denominator and exclusions. Ask how the vendor handles contractual adjustments, refunds, bad debt and vendor-caused write-offs. Otherwise, the company can improve a reported result by removing difficult balances.
First-pass acceptance measures whether a claim passes the receiving system's checks. It doesn't establish correct payment. Under CMS's adopted transaction standards, professional electronic claims use ASC X12N 837 Version 5010; ask how the vendor reconciles submissions, acknowledgments, payer responses and posted payments.
Require drill-down access
Request an anonymized recent reporting package with payer, specialty, provider and aging detail. Our medical billing KPI guide helps distinguish useful operating measures from headline figures.
Consider a hypothetical behavioral health group whose overall collections look healthy while claims with expired authorizations remain unpaid. Only service-level aging and authorization-status reports expose that backlog.
A dashboard should let your administrator identify the unpaid claim, its owner and the next action without scheduling a meeting.
We provide real-time reporting and analytics dashboards alongside eligibility verification, charge capture, certified coding, submission, denial management, A/R recovery and credentialing. Set a working cadence: weekly queue reviews, monthly financial reporting and quarterly decisions recorded in writing.
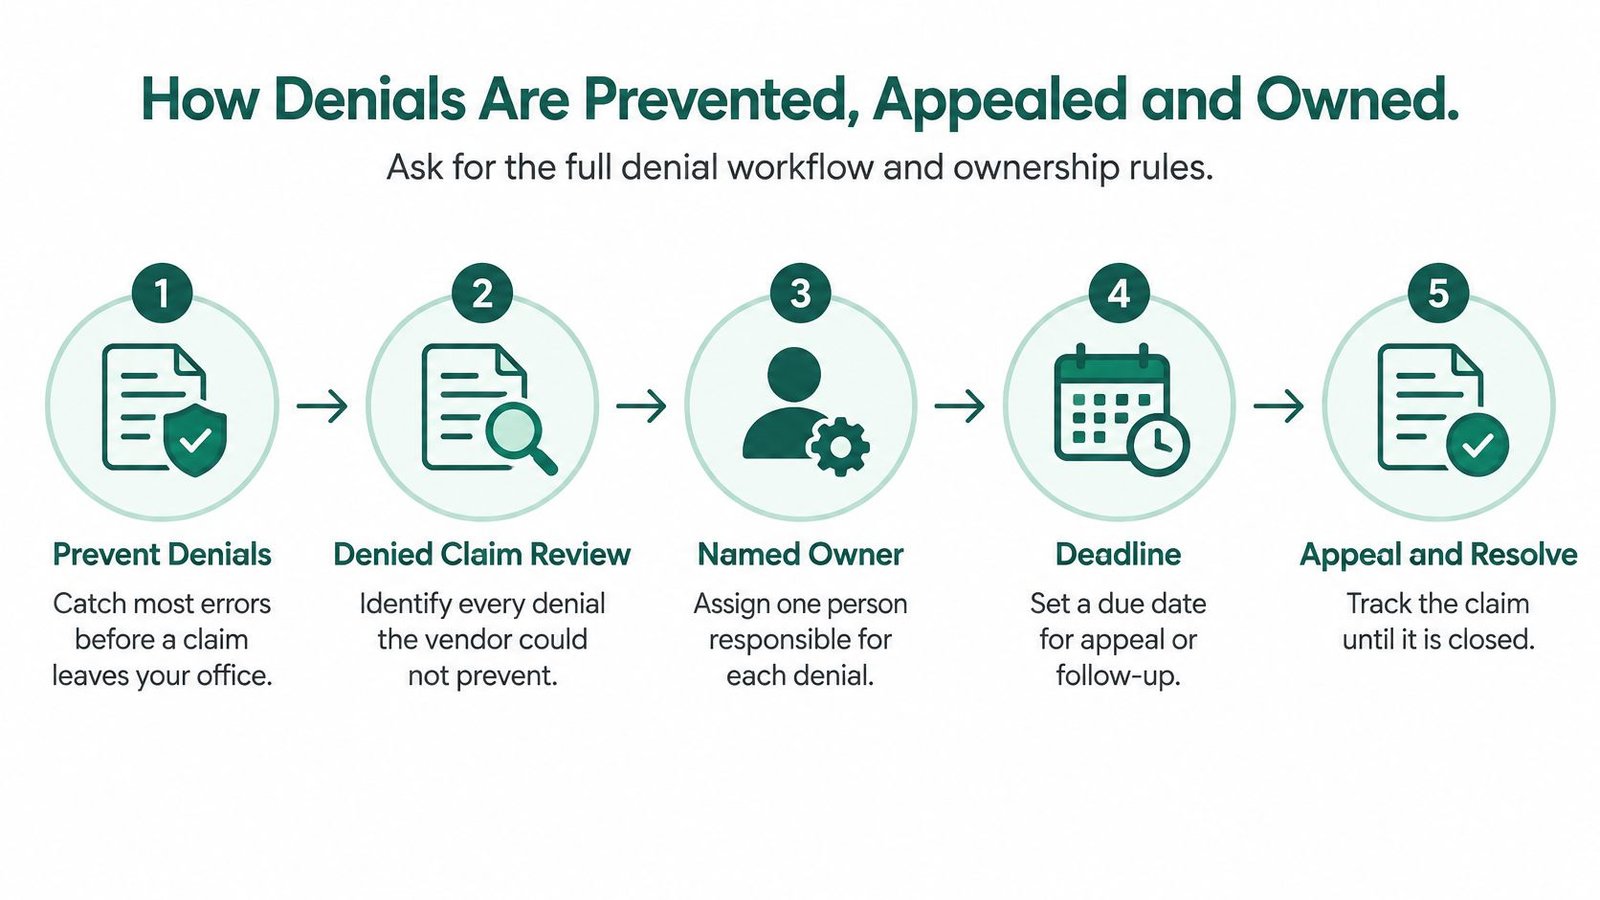
How Denials Are Prevented, Appealed and Owned
A denial does not prove that payment was never owed. Ask the billing company to show how it identifies preventable denials, assigns each case, and tracks the result. Review denial trends by payer, specialty and reason, and compare them with appeal activity and unpaid A/R.
Happy Billing's AI identifies coding mismatches and eligibility issues before a claim leaves the practice's office. When a claim is unfairly denied, Happy Billing fights it with clinical evidence. Ask any prospective partner to explain how staff review AI-flagged issues and who takes responsibility after a payer denies a claim.
Demand a complete workflow
- Classify the response. Separate a rejected claim from an adjudicated denial. The correction or appeal route depends on the response.
- Assign accountability. Identify the person responsible, the deadline and the escalation contact.
- Gather evidence. Collect the clinical documentation and payer correspondence needed to support the case.
- Use the correct route. Submit a correction or appeal through the payer's designated process.
- Record the outcome. Track the reason, decision, payment and any prevention steps needed to stop repeat denials.
CMS Medicare appeals guidance distinguishes rejected Part B claims, which generally can be corrected and resubmitted, from denials that require appeal. It gives 120 days from receipt of the applicable notice or remittance advice to request redetermination.
Use a claim denial management guide to assess whether the vendor can explain its process in operational terms. Ask for counts of denials requested, appealed and overturned by payer and service type. A low appeal count alone says little: it may reflect fewer denials, or a failure to pursue claims that could be paid. A useful answer connects denial reasons and appeal outcomes to unpaid balances and repeat process failures.
Timely Filing and Underpayment Recovery Responsibility
Medicare claims generally must reach the correct contractor within one calendar year after the date of service, and late-filing denials generally aren't initial determinations subject to appeal, according to CMS's timely-filing guidance. An unattended queue can therefore turn a collectible claim into a permanent loss.
Require account-level reporting showing payer, deadline, submission evidence, status and next action. The contract must assign financial responsibility for avoidable vendor-caused losses and disclose those write-offs rather than removing them from performance calculations. Commercial deadlines require payer-specific controls, as illustrated in our UnitedHealthcare timely-filing guide.
Paid doesn't mean paid correctly
Ask whether the company compares paid claims with contracted or otherwise applicable allowed amounts. Our out-of-network underpayment recovery guide explains the owner-level review that separates short payments from legitimate adjustments.
Consider a hypothetical physical therapy practice whose vendor closes every account after receiving a payer payment. Without reconciliation against the expected reimbursement, the owner never learns which accounts merit a dispute.
- Repricing reductions: Ask how the vendor evaluates reductions involving MultiPlan, Zelis and Data iSight/Claritev.
- Eligible disputes: Require a screening process before using the federal IDR process. Not every out-of-network underpayment qualifies.
- Compliance boundaries: Use the No Surprises Act checklist to clarify applicable protections and responsibilities.
Finally, request an anonymized completed recovery showing the original payment, dispute basis, actions and final resolution. Don't accept a recovery total without the underlying work.
Security, BAA and Subcontractor Access to PHI
A signed business associate agreement is necessary, but it isn't proof of effective security. CMS's covered-entity guidance explains the written business-associate agreement requirement and applicable obligations involving agents and subcontractors. Review the agreement before onboarding or transferring PHI.

Request a subcontractor and clearinghouse list, offshore-access locations, a PHI data-flow map, an independent security-assessment summary, audit-log retention details and backup-restoration evidence. Include financial integrations in that review. Lucentive's healthcare accounting software for clinics is relevant when mapping accounting connections, but no software purchase replaces vendor-access diligence.
Test incident response and continuity
Under HHS business-associate guidance, breach notification must occur without unreasonable delay and no later than 60 days after discovery. Negotiate a shorter contractual notification deadline and don't accept notice postponed until an investigation finishes.
- Security evidence: Review access controls, risk assessments and incident-response responsibilities. Encryption alone doesn't settle the question, particularly if keys are compromised.
- Downtime operations: Ask for recovery-time objectives, alternative claim procedures and post-restoration payment reconciliation.
- Cost allocation: Identify who handles forensic work, required notifications and patient support.
HIPAA Journal reports that 807 large healthcare breaches were reported to HHS OCR in 2025, with hacking and IT incidents predominating. Its reporting on HHS OCR breach data also describes the extensive impact of the Change Healthcare incident.
Continuity test: Ask who keeps claims moving when the vendor's normal submission route becomes unavailable.
Contract Length, Exit Terms and Ownership of Your Data
Your contract should let you leave without losing your records or abandoning collectible claims. Ask for the initial term, renewal mechanism, non-renewal notice window and termination-for-cause provisions. Automatic renewal paired with a restrictive notice window deserves legal review before you sign.
Open A/R needs its own transition terms. Establish who works existing claims and appeals, who receives incoming funds, who posts payments and how the departing vendor's access ends. A vague promise to cooperate won't resolve a disagreement over unfinished work.
Run the exit test before onboarding
- Request a sample export. Include claim history, payment detail, adjustments, appeal status and work notes.
- Open the file. Confirm your practice can use it in its management system or a spreadsheet without proprietary software.
- Assign open claims. Identify responsibility for unresolved balances and pending appeals.
- Check renewal mechanics. Put notice dates and delivery requirements on your administrator's calendar.
- Price the transition in the proposal. Require disclosure of any export, assistance or post-termination work charges before signing.
For comparison criteria beyond sales presentations, use our guide to evaluating third-party medical billing companies.
The agreement should also address portal access, record preservation, permitted retention and return or destruction of PHI. Confirm that reporting obligations and service levels continue during transition and survive renewal. Your right to inspect your own financial history shouldn't disappear when the relationship becomes uncomfortable.
How Billing Companies Get Paid and What Each Model Rewards
| Model | How the vendor is paid | What it rewards | What to check |
|---|---|---|---|
| Share of collections | A portion of collected revenue | Collecting more money | Whether smaller and aged balances receive attention |
| Flat monthly service arrangement | Fixed compensation for a defined scope | Predictable cost and workload | Limits on appeals, reporting and credentialing |
| Per-claim or per-transaction arrangement | A charge for specified processing activity | Transaction volume | Treatment of resubmissions and appeals |
| Contingency-only recovery | Payment when money is recovered | Successful recovery | Claim-age, volume and attribution terms |
| Hybrid | Base compensation plus an outcome component | Ongoing work and measured results | Baseline ownership and credit calculation |
The payment model shapes which accounts receive attention. Collection-based compensation can align incentives, but an owner still needs proof that staff work difficult balances rather than only easy payments. A fixed arrangement can offer predictability while leaving expensive appeal work outside the scope.
Ask what happens to credentialing, prior authorization, patient statements, refunds and legacy A/R. For recovery work, define what counts as incremental recovery and how ordinary payer payments are excluded from credited results.
Commercial review: Compare the promised workload and accountability, not just the compensation model's name.
Our out-of-network recovery fees are contingency-only, depend on claim age and volume, and are explained after a free 30-minute call with a billing specialist. We only get paid when we deliver, with nothing upfront.
Use our medical billing outsourcing cost guide to prepare scope questions. Keep the actual proposal separate from general model comparisons, and require complete written commercial terms before committing.
Red-Flag Answers That Should Make You Walk Away
A vendor that repeatedly avoids security, reporting or accountability questions isn't ready for your revenue. Give the company an opportunity to provide evidence. If it still substitutes reassurance for documentation, stop the evaluation.

Test the answer, not the presentation
- Guaranteed total collections: Ask what is excluded. A billing company doesn't control every payer decision, coverage limitation or patient obligation.
- Software catches everything: Request the audit methodology, sample selection and corrective-action records. Automated edits don't replace documented quality review.
- HIPAA compliant without evidence: Ask for the assessment summary and unresolved findings.
- An NDA covers PHI: Request the actual BAA. Confidentiality language doesn't establish the required business-associate obligations.
- No payer-level detail: Ask for an anonymized report. If the vendor can't produce one, you can't independently inspect its revenue decisions.
Look for missing responsibility
- The clearinghouse handles denials: Ask which employee prepares and submits the appeal.
- Audits happen only after payer complaints: Request the proactive review schedule and evidence that findings change workflows.
- Notification follows the completed investigation: Ask when preliminary notice begins and who alerts your practice.
- Owners don't need data access: Request a usable export before proceeding.
- The offer expires before review: Decline the deadline. A legitimate evaluation includes time for counsel and operational checks.
An imperfect answer can be fixed when the vendor acknowledges the gap and commits to a documented correction. Refusal is different. Don't confuse an agreeable salesperson with an accountable operating partner, especially when the unresolved issue affects your ability to recover cash or move your records.
Confirm These Answers Before You Sign
Score each response accepted, conditional or refused. Don't sign with a refusal on security, data export or denial reporting. Conditional answers need an owner and a completion requirement, not a promise to address them after onboarding.

- Collect written answers for every scorecard row.
- Review the BAA and subcontractor disclosures with counsel.
- Inspect sample reports and exports rather than accepting screenshots alone.
- Approve exit terms and responsibility for unfinished claims.
- Document onboarding expectations, baseline metrics, escalation contacts and the account lead.
We can run billing end to end or work alongside your existing biller. Credentialing is separate from billing, so your practice can retain the functions that already work and assign only the gaps.
Bring a recent aging report, an anonymized denial summary and your current scope of services to the discussion. Book a free 30-minute call with a billing specialist to identify the responsibilities your next agreement needs to settle.
US practices only.
Owner Questions About Choosing a Billing Company
Can we keep our current biller and hire you for denials or underpayments?
Yes. We can work alongside your biller, and credentialing can remain separate. Define the queues, handoffs and reporting responsibilities in writing.
What if our vendor already reports a high clean-claim rate?
Ask for payer- and specialty-level results, payment outcomes and exclusions. Acceptance alone doesn't prove that your practice received the correct reimbursement.
How can we check HIPAA protections without an IT team?
Request the BAA, subcontractor list and latest security-assessment summary. Have counsel review the agreement and obtain qualified technical review for unresolved security findings.
What should we do if a vendor refuses denial reports?
Pause the engagement. Require an anonymized sample package before signing or renewing, because you need evidence that someone owns unpaid claims.
Can you handle motor vehicle accident and workers' compensation claims without an EHR change?
Yes, we handle these claims for US practices, end to end or alongside an existing biller. Name them in the scope and confirm workflows inside your current EHR, including eClinicalWorks, Athena Health, EPIC, NextGen or ModMed, without requiring migration.
Happy Billing offers full-cycle billing, credentialing, denial management and targeted recovery alongside your existing team or as an end-to-end partner. Visit Happy Billing to discuss your aging accounts, unresolved denials and the written accountability your practice needs before signing its next agreement.